Will Medicare Pay for a Mobility Scooter: What You’ll Owe
This post contains affiliate links. As an Amazon Associate, we earn from qualifying purchases.
Medicare Part B covers power-operated vehicles (scooters) as Durable Medical Equipment if you have a mobility limitation that significantly impairs your ability to perform activities like toileting, dressing, or bathing in your home, and if a cane, walker, or manual wheelchair cannot meet your need safely. You must have a face-to-face exam and a written prescription from a treating provider within the last six months, and you pay 20% of the Medicare-approved amount after your Part B deductible.
The coverage hinges on the phrase “in your home.” That’s not a suggestion, it’s the legal boundary. Medicare’s policy is built on restoring your ability to move within your residence to perform basic, necessary tasks. A key question is: will Medicare pay for a mobility scooter? A need for mobility outside the home, like going to the grocery store or visiting family, does not qualify on its own. This is the first hurdle where applications stumble.
What follows is a breakdown of the exact medical criteria, the step-by-step bureaucratic path you must navigate, the specific scooter models Medicare will pay for, and the common tripwires that lead to denial when you ask will medicare pay for a mobility scooter. By the end, you’ll know whether your situation fits the federal rules and exactly what paperwork you need to start.
Key Takeaways
- Coverage requires a mobility deficit that prevents specific in-home tasks, not just general difficulty walking. The official term is a limitation in Mobility-Related Activities of Daily Living (MRADLs).
- You pay 20% coinsurance after your Part B deductible if your DME supplier accepts assignment; using a non-participating supplier can cost you significantly more.
- The process is a sequence, not a suggestion: a face-to-face exam starts a 6-month clock for your doctor to write the Standard Written Order, which must be in the supplier’s hands before the scooter is delivered.
- Scooter specs are federally regulated. Medicare-covered models, identified by HCPCS codes like K0800 or K0807, must meet exact size, speed, and range requirements, a retail “mobility scooter” might not qualify.
- Replacement before 5 years is nearly impossible unless the original scooter is lost or destroyed in a specific accident or natural disaster.
What Does “Medically Necessary” Actually Mean for a Scooter?
Forget “my knees are bad” or “I get tired walking.” The will medicare pay for a mobility scooter question requires a surgical definition of medical necessity. To qualify, you must have a mobility limitation that “significantly impairs” your ability to participate in one or more Mobility-Related Activities of Daily Living (MRADLs) inside your home. The list is short and specific: toileting, feeding, dressing, grooming, and bathing.
A mobility limitation is one that: prevents the activity entirely, places you at a heightened risk of injury, or prevents you from completing the activity within a reasonable time frame.
The reality is this. Needing a scooter to go to the park doesn’t count. Needing it because you cannot safely walk from your bed to the toilet without falling, that’s the kind of deficit Medicare looks for. The evaluation also requires proving that a cane or walker cannot resolve this deficit safely. If you can manage with a simpler aid, even if it’s difficult, coverage will be denied.
Where this goes sideways: Doctors sometimes write prescriptions based on a patient’s general quality-of-life needs. Medicare reviewers look for explicit documentation linking the mobility deficit to the specific in-home MRADLs. A prescription that says “patient needs scooter for mobility” will be rejected. It must state why and for what home-based activity.
The Crucial “In-Home Use” Requirement

This is the most misunderstood rule. The scooter must be deemed necessary for use inside your home to perform these MRADLs. A Reddit user in the r/disability community put it bluntly: “My doctor had to prove I needed it IN my house, not going out in the world. They won’t cover for outside but they will for inside.”
Official CMS criteria require the device to be needed for use in the home to perform MRADLs, while a Medicare.gov publication suggests a doctor or supplier may verify the home environment can accommodate the device. This isn’t a casual check; it’s part of the documentation. If your home isn’t accessible, Medicare’s stance is that the scooter isn’t reasonable and necessary for that setting.
What Are the Steps to Get a Scooter Covered?
The path from doctor’s visit to delivery is a chain of paperwork with strict deadlines. Break one link, and the claim is denied. It’s less like buying medical equipment and more like executing a legal contract.
- The Face-to-Face Encounter: You must have an in-person visit with a physician, physician assistant, nurse practitioner, or clinical nurse specialist. This visit must occur within six months before the scooter is ordered. The medical record must show that a mobility examination was a major reason for the visit.
- The Standard Written Order (SWO): After the exam, your treating provider must write a detailed prescription. This SWO must include your name, the date of the exam, the specific diagnoses, a description of the needed scooter, the length of need, and the provider’s signature and date. A power mobility device may not be ordered by a podiatrist.
- Supplier Selection & Assessment: You must use a DME supplier enrolled in Medicare. That supplier must have a RESNA (Rehabilitation Engineering and Assistive Technology Society of North America) certified professional conduct an in-person assessment to help select the appropriate device. This assessment must happen after the face-to-face encounter begins.
- Prior Authorization: For certain types of power wheelchairs, the supplier must get an approved prior authorization from Medicare before delivery. If a supplier delivers an item prior to receipt of a Written Order Prior to Delivery (WOPD), it will be denied as not reasonable and necessary, and payment will not be made even if a WOPD is subsequently obtained.
- Delivery & Payment: The supplier must have the Written Order Prior to Delivery (WOPD) before delivering the scooter. If a supplier delivers an item prior to receipt of a Written Order Prior to Delivery (WOPD), payment will not be made even if a WOPD is subsequently obtained. Once delivered, you are responsible for the 20% coinsurance (after your Part B deductible) if the supplier accepts assignment.
| Step | Who Does It | Key Deadline | Consequence If Missed |
|---|---|---|---|
| 1. Face-to-Face Exam | Treating Practitioner (MD, PA, NP, CNS) | Within 6 months of order | Claim denial; device not covered. |
| 2. Standard Written Order | Same Treating Practitioner | After exam, before delivery | No valid prescription; supplier cannot bill. |
| 3. Supplier Assessment | RESNA-certified pro at DME supplier | After face-to-face process starts | Invalidates device selection; can lead to denial. |
| 4. Prior Authorization | DME Supplier (for certain devices) | Before delivery | Claim automatically denied. |
| 5. Delivery w/ SWO in Hand | DME Supplier | Must have SWO prior to delivery | Payment refused, even if SWO is obtained later. |
Common mistake: Thinking the doctor’s prescription is the finish line. It’s just the baton pass to the supplier, who has their own set of federally mandated steps to complete. If the supplier is slow or disorganized, your 6-month clock from the doctor’s visit can run out.
How Much Will Medicare Pay and What Do You Owe?

Medicare Part B pays 80% of the Medicare-approved amount for the scooter after you meet your annual Part B deductible (which changes yearly). You are responsible for the remaining 20% coinsurance.
The critical variable is your DME supplier. If the supplier participates in Medicare, they are required to accept “assignment.” This means they agree to the Medicare-approved amount as full payment, charging you only the deductible and coinsurance. If the supplier is non-participating but still enrolled, they can choose whether to accept assignment on a case-by-case basis. If they don’t accept assignment, they can charge you up to 15% more than the approved amount, and you may have to pay the full cost upfront and seek reimbursement from Medicare later.
Bottom line: Always ask your supplier, “Do you participate in Medicare and accept assignment?” before you agree to anything. Getting a free scooter or an offer to waive your copayment is a classic sign of fraud, according to official Medicare publications.
For a sense of the potential cost, consider that the scooter itself is just one part. The 20% coinsurance applies to the base device and any Medicare-approved accessories.
What Are the Medicare-Approved Scooter Specs?
Medicare doesn’t just cover any scooter. It covers specific devices that meet exact performance standards, categorized by HCPCS codes. These are not retail model names; they are billing codes that correspond to a set of federal specifications. If a scooter doesn’t meet these specs, it won’t get a K-code, and Medicare won’t pay for it.
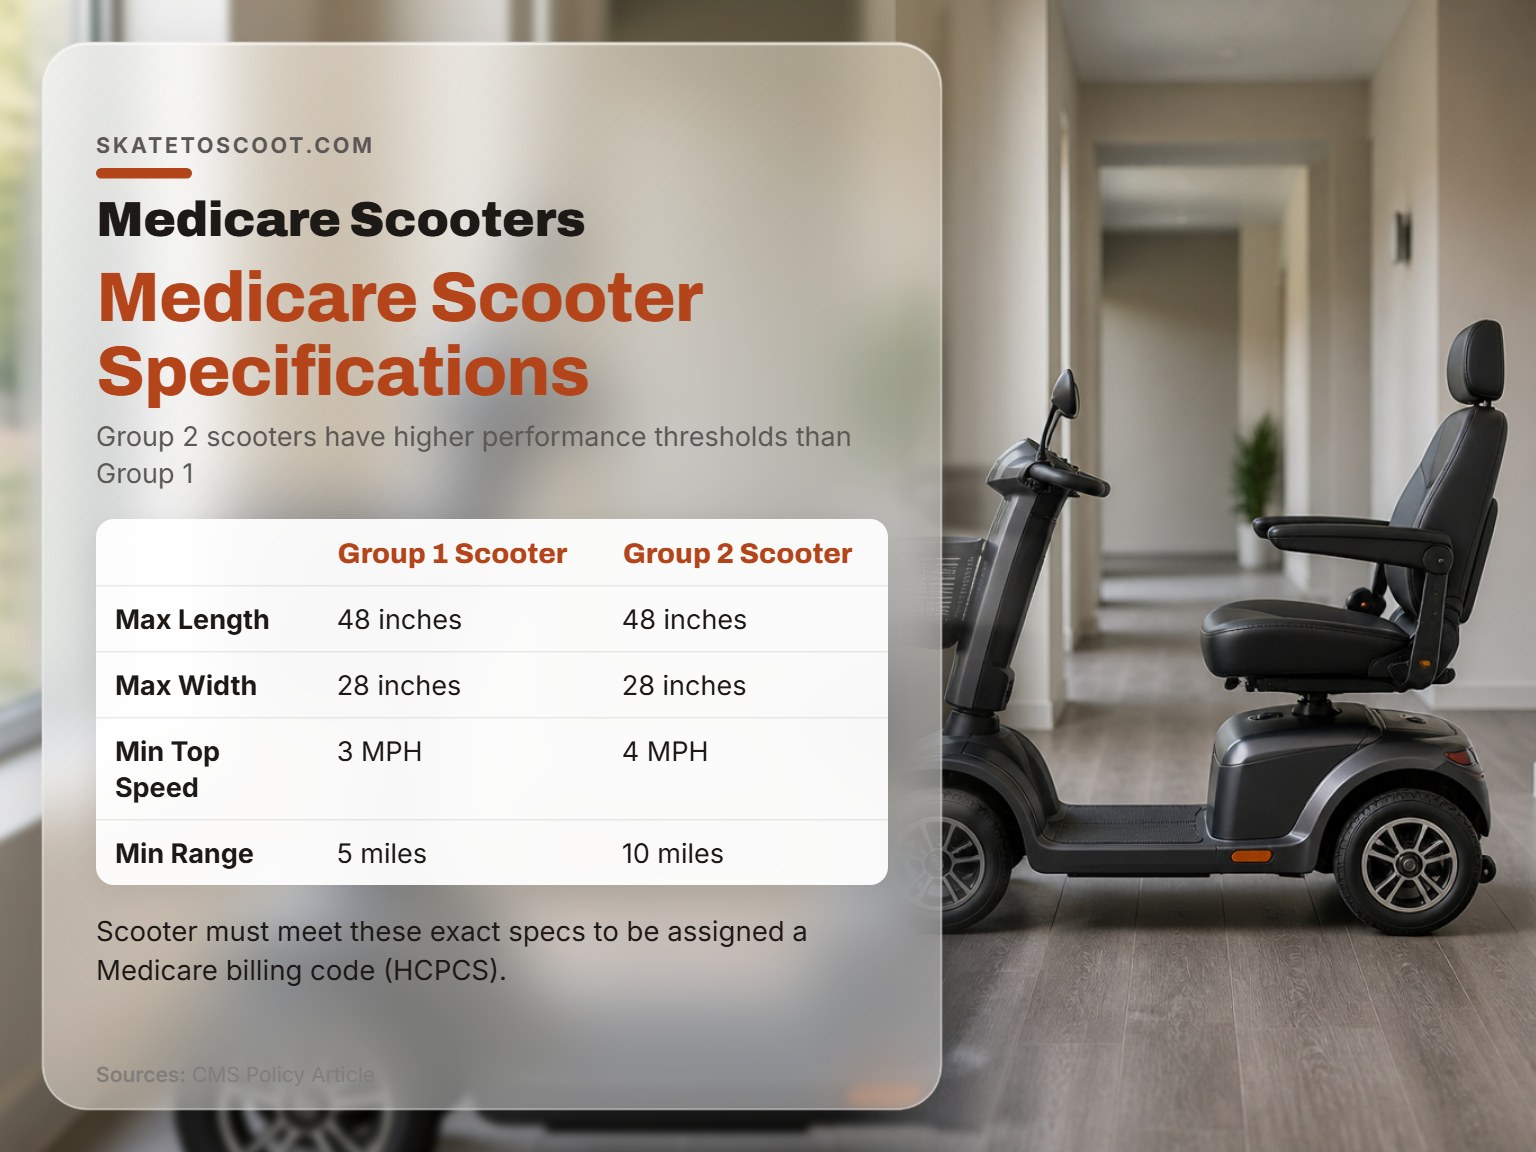
The two main groups are Group 1 and Group 2 Power Operated Vehicles (POVs). Group 2 scooters have higher performance thresholds.
| Specification | Group 1 POV (e.g., K0800, K0801, K0802) | Group 2 POV (e.g., K0806, K0807, K0808) |
|---|---|---|
| Maximum Length | 48 inches | 48 inches |
| Maximum Width | 28 inches | 28 inches |
| Minimum Top Speed | 3 MPH | 4 MPH |
| Minimum Range | 5 miles | 10 miles |
| Minimum Obstacle Climb | 20 mm | 50 mm |
| Maximum Pivot Turn Radius | 54 inches | 54 inches |
| Weight Capacity (Standard/Heavy Duty) | 300 lbs / 301-450 lbs | 300 lbs / 301-450 lbs |
These specs come straight from the CMS Power Mobility Devices policy article (A52498). Suppliers use these codes to bill Medicare. For example, a K0801 is a Group 1 heavy-duty scooter with a weight capacity of 301-450 pounds. Knowing these codes helps you verify that the scooter your supplier is providing actually qualifies under the official Medicare DME coverage criteria.
The Weight Class Trap

Here’s a non-commodity insight straight from the CMS manual: To qualify for a scooter in a given weight class, your weight must not only be under that class’s maximum capacity, but also at least 95% of the maximum capacity of the next lower weight class. This creates a coverage gap.
To qualify for a scooter in a given weight class, your weight must be ≤ the device’s max capacity AND ≥95% of the weight capacity of the next lower POV weight class. This precise, bureaucratic rule is why a thorough assessment by the supplier’s RESNA-certified professional is essential.
What Are the Most Common Reasons for Denial?
Understanding why claims fail is the best way to avoid it. Denials aren’t random; they’re failures to meet specific, documented rules.
- Lack of Medical Necessity for In-Home MRADLs: This is the big one. The documentation didn’t convincingly show that your mobility deficit prevents specific activities (toileting, dressing, etc.) inside your home.
- Missing or Incomplete Face-to-Face Documentation: The doctor’s notes don’t prove the exam happened, don’t show the mobility exam was a major reason for the visit, or are older than six months.
- Supplier Delivered Without a SWO: If the scooter arrives at your door before the supplier has the signed, detailed Standard Written Order, the claim is dead on arrival. This is a hard rule in CMS policy.
- Prior Authorization Not Obtained: For devices that require it, this is a mandatory pre-check. Skipping it guarantees denial.
- Environmental Incompatibility: The assessment couldn’t verify that your home layout can safely accommodate the scooter’s use, storage, and charging.
If you are denied, you have the right to appeal. The denial notice will explain how. The first level is a “redetermination” request to the Medicare Administrative Contractor that made the initial decision.
Renting, Replacing, and Other Edge Cases
Renting vs. Buying: For scooters, Medicare typically pays via a “purchase” model because they are considered Durable Medical Equipment. The reasonable useful lifetime of DME, as defined by the Social Security Act, is 5 years. Medicare will not pay for a replacement scooter within that 5-year period unless the original is lost or irreparably damaged in a specific, documented accident or natural disaster (like a fire or flood). If a POV or power wheelchair is a replacement during the 5-year useful lifetime of an item previously covered, a new face-to-face encounter is not required.
Caregiver Operation: This is a critical distinction between scooters and power wheelchairs. For a power wheelchair, if you cannot operate it yourself, a caregiver may operate it for you, provided you also cannot self-propel a manual chair and have no willing caregiver to push a manual chair. For a scooter (POV), the beneficiary must be able to safely operate and get on and off the device independently; the caregiver operation exception that applies to power wheelchairs does not apply to POVs.
What if my needs change?
How does Medicare decide between a scooter, a cane, or a manual wheelchair?
Medicare’s coverage rules are a strict hierarchy. A mobility scooter is not approved simply because walking is difficult. You must first prove that a cane or walker cannot safely and sufficiently resolve your mobility limitation. If you can manage at home with a simpler aid, Medicare will not cover a scooter. For a manual wheelchair, the rules consider whether you or a willing caregiver can physically propel it. A key difference is that a caregiver is allowed to operate a covered power wheelchair for you, but Medicare explicitly prohibits a caregiver from operating a covered scooter; you must be able to get on, off, and drive it independently.
What’s the difference between Medicare and Medicaid coverage for a scooter?
Medicare and Medicaid are separate programs with different rules. Medicare Part B covers a scooter as Durable Medical Equipment if you meet its specific clinical criteria for use in the home. You typically pay 20% of the approved cost after your deductible. Medicaid is a state-run program for people with limited income and resources, and its coverage rules, including prior authorization steps and cost-sharing, vary significantly by state. Medicare Part B coverage requires the device to be needed for use in the home to perform MRADLs. Medicaid, a state-run program, may have different requirements, and some anecdotal reports suggest it may include a formal home environment verification.
Frequently Asked Questions
What mobility scooters are covered by Medicare?
Medicare covers Power Operated Vehicles (POVs) that are prescribed as Durable Medical Equipment and meet specific federal specifications, identified by HCPCS codes K0800, K0801, K0802 (Group 1) and K0806, K0807, K0808 (Group 2). These codes correspond to exact size, speed, range, and weight capacity standards, not retail brand names.
Can seniors get a free mobility scooter?
Medicare does not provide “free” scooters. You are responsible for the Part B deductible and 20% coinsurance. Be extremely wary of anyone offering a free scooter, waiving your copayment, or paying you cash, these are listed by Medicare as classic signs of fraud. Legitimate assistance may be available through state Medicaid programs or local non-profits, but these have their own strict eligibility rules.
How do I get Medicare to pay for an electric scooter?
You must follow the step-by-step coverage process: have a face-to-face exam documenting a medical need for in-home mobility, get a detailed Standard Written Order from that provider, choose a Medicare-enrolled DME supplier who completes a RESNA assessment, and ensure all paperwork (including prior authorization if needed) is complete before the scooter is delivered. There are no shortcuts.
How much will Medicare pay on a mobility scooter?
Medicare Part B will pay 80% of the Medicare-approved amount for the scooter after you meet your yearly Part B deductible. You pay the remaining 20%. The amount you pay depends on whether your supplier accepts assignment. If a DME supplier does not accept assignment, they may charge you more than the Medicare-approved amount.
Before You Go
Getting a mobility scooter covered by Medicare is a procedural marathon, not a sprint. The system is designed to filter out requests that don’t meet a narrow, home-centric definition of medical necessity. Your success depends almost entirely on the quality and specificity of the documentation from your doctor and your DME supplier.
But if your challenge is truly about performing basic, necessary functions within your own home, and you can document it precisely, this path exists.
One final, practical rule: start the conversation with your doctor by naming the specific in-home activity you struggle with, not by asking for a scooter. Frame it as, “I cannot safely get from my bed to the toilet without a high risk of falling,” not “I need a scooter.” That aligns your need directly with Medicare’s clinical criteria and sets the stage for the documentation you’ll need. Everything else, the codes, the assessments, the prior auth, is just paperwork following that fundamental point.
